At a glance
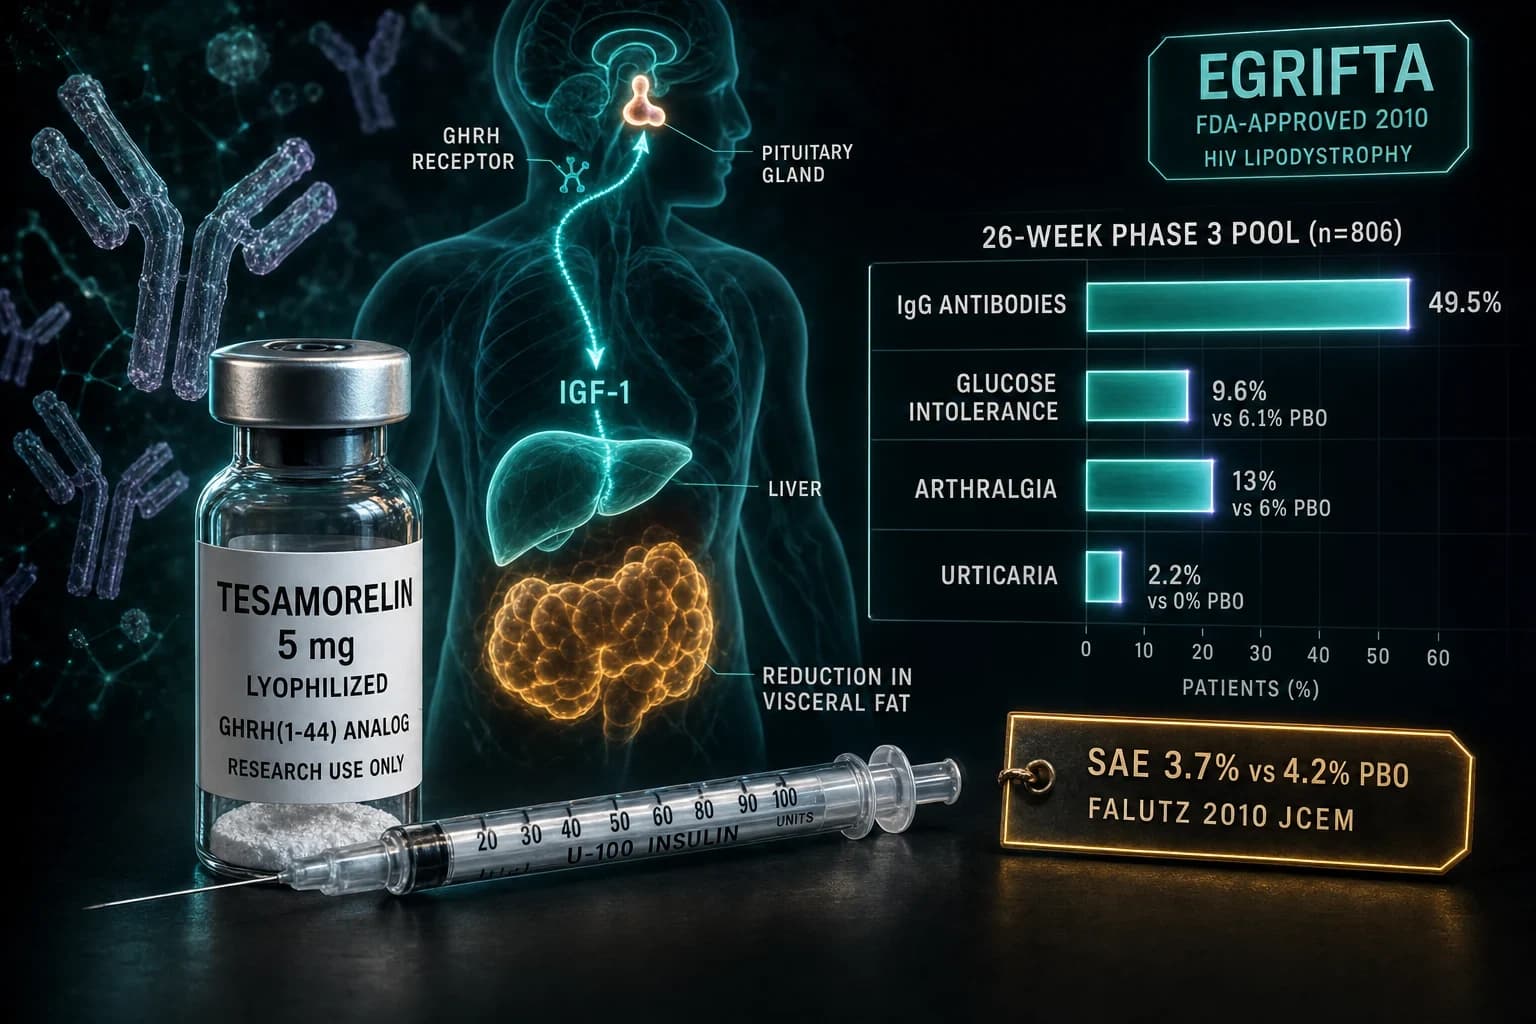
- Anti-tesamorelin IgG antibodies developed in 49.5% of patients at 26 weeks; most were clinically silent.
- 2.2% of Phase 3 patients developed urticaria after 4-5 months of therapy; all six tested IgG positive and discontinued.
- New-onset glucose intolerance ran 9.6% on tesamorelin vs 6.1% on placebo in the pooled Phase 3 (Falutz 2010, PMID 20554713).
- Serious adverse event rates were 3.7% tesamorelin vs 4.2% placebo across 806 subjects over 26 weeks.
- A 12-week trial in stable type 2 diabetes (Clemmons 2017, PMID 28644810) showed no change in HbA1c or diabetes control.
Most tesamorelin "side effects" pages recycle the same list of eight bullet points without a single trial-level number. The actual Phase 3 safety file reads differently. Across 806 HIV patients randomized to 2 mg daily or placebo for 26 weeks and then followed for another 26, serious adverse events ran 3.7% on tesamorelin and 4.2% on placebo (Falutz et al. 2010). The signal that split the arms was not catastrophic events. It was two slower patterns: an IgG antibody response in roughly half of treated patients, and a smaller excess of new glucose intolerance in the treated arm. Everything else on the label is downstream of those two, plus the predictable injection-site reactions you get with any daily subcutaneous research peptide.
This article walks the real adverse-event picture at the depth the trial record supports. For the compound's mechanism, approved indication, and visceral-fat efficacy data, the tesamorelin visceral fat guide and the tesamorelin dosage chart cover those sides. This piece is strictly the safety side, built from the published Phase 3 pool and the follow-up studies in type 2 diabetes and non-HIV obese adults.
Bottom line: Tesamorelin's dominant observed side effects are injection-site reactions and arthralgia. The two signals that matter for risk-adjusted use are the IgG antibody response (which can turn into clinically important urticaria in roughly 2% of long-term users) and a small excess of new glucose intolerance (about 3.5 percentage points above placebo over 26 weeks). Pre-existing uncontrolled diabetes, active malignancy, and pregnancy are the contraindications the label takes seriously, and nothing in the research record argues with them.
The 806-patient Phase 3 safety signal in one table
The two pivotal trials behind the 2010 FDA approval were CTR-1011 and CTR-1012. The first was published as Falutz et al. 2007 in NEJM: 412 HIV patients, 26 weeks, visceral adipose tissue down 15.2% vs placebo up 5.0%, no significant glycemic differences on the primary endpoint. Both pivotal trials ran a 26-week safety extension in which placebo subjects crossed over to tesamorelin and treated subjects were re-randomized to continue or switch to placebo. The pooled population was 806 HIV patients with excess abdominal fat, mean age 48, 86% male. The Falutz et al. 2010 pooled analysis in JCEM is where the comparative safety numbers come from.
| Signal | Tesamorelin 2 mg | Placebo | Notes |
|---|---|---|---|
| Serious adverse events, 26 wk | 3.7% | 4.2% | No excess attributable to drug |
| Discontinuation for adverse event, 26 wk | 11.8% | 7.6% | Driven by arthralgia, swelling, injection-site reactions |
| New glucose intolerance (any-cause) | 9.6% | 6.1% | Captured as fasting glucose shift or OGTT impairment |
| Urticaria beyond injection site | 2.2% (6/273) | 0% | Appeared at month 4 to 5; all 6 were IgG positive |
| Peripheral edema | 6% | 2% | Dose-related; GH-axis signature |
| Arthralgia | 13% | 6% | Hands, wrists, knees; GH-axis signature |
| Injection-site erythema or pruritus | ~25% combined | ~10% | Most-common complaint overall |
| Anti-tesamorelin IgG antibodies, 26 wk | 49.5% | n/a | FDA label; mostly clinically silent |
| Anti-tesamorelin IgG antibodies, 52 wk | 47.4% | n/a | Steady-state, not progressive |
| Mean fasting glucose change | +4 mg/dL | +1 mg/dL | Difference non-significant on primary endpoint |
Read the table left-to-right rather than top-to-bottom. The columns that split meaningfully are glucose intolerance, urticaria, and the GH-axis fluid-retention cluster (edema, arthralgia, carpal tunnel symptoms). The columns that look alarming at first (SAE rate, discontinuations) land close to placebo once you remove patients who stopped for reasons unrelated to the drug.
The IgG antibody story most vendor pages skip
Tesamorelin is a 44-amino-acid peptide carrying a trans-3-hexenoic acid group at the N-terminus. That modification is what makes the molecule resistant to DPP-4 cleavage and gives it a half-life long enough for once-daily dosing. It also makes the peptide immunogenic at a different level than endogenous GHRH.
In the combined Phase 3 trials, anti-tesamorelin IgG antibodies were detected in 49.5% of patients at 26 weeks and 47.4% at 52 weeks (EGRIFTA FDA label, 2010). The antibody response was not progressive: it reached roughly half the treated population and stayed there. Most of those patients had no clinical correlate. Serum IGF-1 continued to rise. Visceral fat continued to fall. The antibodies, in most cases, bound tesamorelin without neutralizing it.
The subset that mattered was small and specific. Six of 273 patients in the first Phase 3 (2.2%) developed urticaria that extended beyond the injection site, appearing 4 to 5 months into treatment. All six tested positive for anti-tesamorelin IgG. All six discontinued per protocol. In the FDA's analysis of the hypersensitivity subset across the full program, 85.2% of patients with hypersensitivity were IgG positive. That is the mechanistic link the label flags: not an acute first-dose anaphylaxis, but a delayed, antibody-mediated urticaria that shows up after several months.
Two practical implications. First, a researcher who sees generalized urticaria on tesamorelin at month 4 or 5 should take it seriously; it is not a nuisance reaction. Second, an uncomplicated first month tells you very little about whether this patient will develop antibodies by month 6, because the median onset is later than almost any other peptide adverse event.
Injection-site reactions, the leading complaint
Daily subcutaneous administration of a 2 mg peptide produces injection-site reactions in a large minority of patients. In the Phase 3 pool, erythema, pruritus, pain, irritation, and bruising at the injection site were the most-common adverse events on the drug side, affecting roughly a quarter of treated patients cumulatively over 26 weeks. Most were mild, resolved spontaneously, and did not drive discontinuation.
Site rotation is standard. The abdominal subcutaneous route is the labeled site; rotating the exact spot each day inside a hand-sized abdominal zone keeps any single injection path from accumulating a reaction. For the mechanics of reconstitution and site handling, our reconstitution calculator and the broader bacteriostatic water vs sterile water write-up cover the diluent and vial-handling questions that drive about half of what people call "injection-site reactions" when the real cause is contamination or poor technique.
A separate point worth naming: the EGRIFTA 1 mg formulation (which has a different reconstitution volume) and the EGRIFTA SV formulation (sucrose-free, 1 mg) were both associated with injection-site reactions at similar rates in post-marketing surveillance. The site-reaction signal is a function of the molecule and the daily subcutaneous route, not a specific excipient.
Arthralgia and the fluid-retention cluster
Tesamorelin raises GH pulse amplitude, GH raises IGF-1, and IGF-1 at sustained supra-baseline levels pulls fluid into soft tissues. The downstream reactions you see on the label (arthralgia, peripheral edema, carpal tunnel symptoms, myalgia, paresthesia) are the same cluster you see on recombinant HGH, at smaller absolute magnitudes because the pituitary still enforces somatostatin feedback.
The Phase 3 absolute rates were arthralgia 13% vs 6% placebo, peripheral edema 6% vs 2%, and carpal tunnel symptoms around 1% to 2% in treated subjects. Hand and wrist joints are the most-common location, consistent with the GH signature. The pattern typically appears within the first 8 to 12 weeks of therapy and is dose-related. Most cases are mild and self-limited; a subset drives discontinuation. In the trials, arthralgia and swelling were the two most-common reasons patients stopped the drug for adverse events.
If a researcher sees new wrist pain, grip weakness, or morning hand stiffness in the first 2 to 3 months, the GH-axis fluid signature is the leading hypothesis before any musculoskeletal workup. Dose reduction has not been formally studied, because the approved dose is a single 2 mg daily tier.
The GH-axis mechanism is also why combination protocols with a ghrelin-receptor agonist require more caution than either compound alone. For how tesamorelin stacks with and differs from the ghrelin side of the GH axis, the tesamorelin vs ipamorelin comparison walks the pharmacology and the overlap in adverse-event profile.
The glucose watch: 9.6% vs 6.1% new-onset glucose intolerance
The single most-cited concern with any GHRH-axis compound is glucose. Growth hormone opposes insulin at the hepatic level, so a sustained rise in GH pulse amplitude could in principle worsen glucose tolerance. The Phase 3 pool is where this concern became a specific number.
New-onset glucose intolerance (fasting glucose shift into the impaired range, or an impaired 2-hour oral glucose tolerance test) was captured in 9.6% of tesamorelin patients vs 6.1% of placebo patients in the pooled 26-week analysis. The absolute 3.5-percentage-point difference did not translate into clinically meaningful HbA1c changes on the group average, but it was large enough that the FDA label carries a dedicated glucose-monitoring recommendation.
Pre-marketing, the signal was not dose-dependent at the single 2 mg tier studied. Post-marketing, the pattern has held: tesamorelin can shift a patient already on the edge of impaired fasting glucose into frank impairment, without consistently driving a confirmed new type-2 diabetes diagnosis. The practical implication is a baseline fasting glucose and HbA1c at week 0, a repeat at week 12, and a lower threshold for stopping if the trajectory is wrong.
What the type 2 diabetes safety study added (Clemmons 2017)
The population the Phase 3 trials deliberately excluded was patients with diagnosed, treated type 2 diabetes. Those patients came back into the record through a dedicated 12-week safety study (Clemmons et al. 2017) in 53 adults with stable type 2 diabetes on oral agents or basal insulin. Patients were randomized to placebo, 1 mg, or 2 mg daily.
At week 12, HbA1c, fasting glucose, and overall diabetes control did not differ significantly between the groups. No patient discontinued the study for loss of diabetes control. Modifications to diabetes medications were comparable across arms. The 2 mg group showed a modest decrease in total and non-HDL cholesterol versus placebo, consistent with the lipid signal from the HIV Phase 3.
This is the strongest evidence against a straightforward glucose-decompensation story in people already on diabetes therapy. It is also only 12 weeks and 53 patients, so it does not establish long-term safety in that population. Pre-existing uncontrolled diabetes remains a contraindication; stable, well-controlled diabetes on treatment was the Clemmons cohort and tolerated the drug.
Non-HIV obese adults at 12 months (Makimura 2012)
The other population worth naming is non-HIV abdominally obese adults with relative GH deficiency. A 12-month randomized trial of 60 such subjects on tesamorelin 2 mg daily vs placebo (Makimura et al. 2012) is the longest controlled safety exposure in a non-HIV population published to date.
Visceral adipose tissue dropped 16 cm² on tesamorelin vs an increase of 19 cm² on placebo. IGF-1 rose significantly in the treated group. Fasting glucose, 2-hour glucose, and HbA1c did not differ meaningfully between arms over the full year. Carotid intima-media thickness and triglycerides improved. The adverse-event pattern (injection-site reactions, mild arthralgia, no SAE excess) replicated the HIV Phase 3 at longer exposure in a different population.
This study is the main published evidence that the Phase 3 safety profile is not an HIV-specific artifact driven by concurrent antiretroviral therapy, and that 12 months of continuous dosing does not degrade the signal. A separate 50-patient randomized trial by Stanley et al. 2014 in JAMA extended the picture into liver fat: at 6 months, tesamorelin reduced hepatic fat fraction and visceral fat without an excess of adverse events over placebo, which is the clearest evidence that the GH-axis signal does not translate into hepatic injury in the populations tested.
Theoretical and label-level warnings worth taking seriously
Several warnings on the EGRIFTA label do not appear in trial-level incidence tables because the trials deliberately excluded the relevant populations. They are not weak claims; they are the standard GH-axis contraindications.
- Active malignancy. Tesamorelin raises IGF-1. IGF-1 is mitogenic. Any active cancer, in treatment or not fully resolved, is a hard contraindication. The trials excluded active malignancy.
- Pregnancy and lactation. No controlled pregnancy data exist. The GH axis is pregnancy-active, so the label advises against use in pregnancy, and no researcher should run tesamorelin in a patient who could become pregnant without a documented plan.
- Pediatric populations. Not studied, not approved; GH-axis manipulation in children belongs to pediatric endocrinology and recombinant HGH or sermorelin protocols, not to a drug approved for HIV lipodystrophy in adults.
- Acute critical illness. The GH axis changes substantially in sepsis, major trauma, and ICU-level respiratory failure. Clinical trials of rhGH in critical illness showed excess mortality. Tesamorelin was not studied in this setting and the label specifically cautions against initiation.
- Hypopituitarism. Pituitary somatotroph reserve has to exist for GHRH analogs to work. Hypopituitarism is both a reason the drug may not work and, in the acute setting, a reason to avoid provoking an incomplete axis.
- Diabetic retinopathy. rhGH is contraindicated in active proliferative retinopathy. The signal is weaker for GHRH analogs because the IGF-1 rise is smaller and feedback-limited, but the label still cautions against use in this population.
For contrast on how a related GHRH-axis peptide handles the same contraindication list at a shorter half-life and smaller IGF-1 excursion, the sermorelin side effects breakdown walks the parallel case. The sermorelin vs tesamorelin analog comparison covers how the two differ at the pharmacokinetic level that drives these risk differences.
What a responsible research protocol would monitor
The published trial record points to a short, specific monitoring list rather than a long one:
- Baseline and week-12 fasting glucose and HbA1c. The 3.5-percentage-point excess in new glucose intolerance is the single most-reproducible safety signal and the easiest to catch early.
- Baseline IGF-1 and a repeat at week 12. Not for efficacy; for safety. An IGF-1 that climbs above the upper reference range at 2 mg daily is a signal to pause and reassess rather than continue.
- Awareness of month 4 to 6 urticaria. The IgG-mediated hypersensitivity window is specific and not something a researcher would notice without expecting it. New generalized urticaria at this timepoint is a reason to stop, not to continue through.
- Hand and wrist symptom check at weeks 4, 8, and 12. The GH-axis fluid-retention cluster is dose-related, mostly early, and resolves on discontinuation. Catching it early reduces the small number of protocol-ending events.
- Injection-site rotation. Standard, boring, and the single intervention that reduces the most-common adverse event.
Lab test documentation for research peptide batches, including purity and identity verification for tesamorelin lots, lives in the Peptides:Enhanced lab tests library. Any serious research protocol should start by confirming the batch and lot it is actually dosing. For how we evaluate the full vendor supply chain (identity, purity, consistency across lots), the Ascension Peptides review walks the audit at the depth most vendors do not survive (code ENHANCED applies 50% off at Ascension if the review stands up for your workflow). Ascension carries tesamorelin as a 5 mg lyophilized research vial under the slug tesamorelin-5mg.
What this profile is not
Three framings worth refusing explicitly:
- "Tesamorelin is the safest peptide." It is not. It is one of the better-documented peptides because it was taken through an FDA Phase 3 program and has a public label. Documentation is not the same as safety. The IgG antibody signal, the glucose shift, and the GH-axis fluid cluster are all real at trial-level incidence.
- "The side-effect profile matches recombinant HGH." It does not. Mean absolute magnitudes are smaller because the pituitary feedback loop stays intact. The qualitative pattern (fluid retention, arthralgia, glucose shift) is the GH signature, but tesamorelin is a milder expression of that signature than rhGH at equivalent IGF-1 exposure.
- "If my first month is clean I'm clear." The month-4-to-5 urticaria onset makes short-term tolerability a weak predictor of long-term tolerability. The practical minimum observation window for a tesamorelin tolerability call is roughly 6 months of continuous dosing, not 4 weeks.
Bottom line: The research-grade decision on tesamorelin is not whether side effects exist (they do, in documented proportions) but whether the known profile is acceptable for the specific endpoint being studied. For the visceral-fat endpoint the drug was approved on, the risk-benefit was favorable enough for FDA approval in a specific population. Outside that population, the same safety data applies and the benefit case is the open question.
Related reading
- Tesamorelin visceral fat guide: the GHRH analog clinical record
- Tesamorelin dosage chart with reconstitution math
- Tesamorelin vs ipamorelin: GHRH analog vs ghrelin agonist
- Tesamorelin vs CJC-1295: head-to-head on the GHRH side
- Sermorelin vs tesamorelin GHRH analog comparison
- Sermorelin side effects, the shorter-acting GHRH comparison
- Ascension Peptides review: how we audit a research-grade vendor
- Peptides:Enhanced lab-test library for independent identity and purity data
Research purposes only. Tesamorelin is approved by the FDA (EGRIFTA and EGRIFTA SV) only for the reduction of excess abdominal fat in HIV patients with lipodystrophy. It is not approved as a weight-loss drug, a body-composition drug, or a growth-promoter in any other population. Nothing in this article is medical advice, a treatment protocol, or an endorsement of self-administration. Discuss any decision about this compound with a qualified clinician.